Ulcers are a leading reason for hospital admission and amputation in diabetes. Early assessment is one of the few parts of that pathway patients can influence directly.
01
Why these ulcers form
Neuropathy reduces feeling and can change the shape of the foot. Repeated pressure under a metatarsal head or a toe then splits the skin. If arteries are also narrowed, the wound receives less oxygen and fewer of the cells needed for repair. Infection can then move into tendon or bone.
02
Warning signs
- A blister or callus with fluid or blood under it
- An open area on the sole, heel, or between the toes
- Redness streaking up the foot
- A sweet or foul smell
- Black tissue
- Fever or a sudden rise in blood glucose
03
When to seek assessment
Arrange care as soon as an ulcer is seen. Do not wait for the next routine diabetes visit if the wound is open. Emergency care is appropriate for fever, spreading redness, black skin, or a foot that has become cold.
04
How an ulcer is usually evaluated
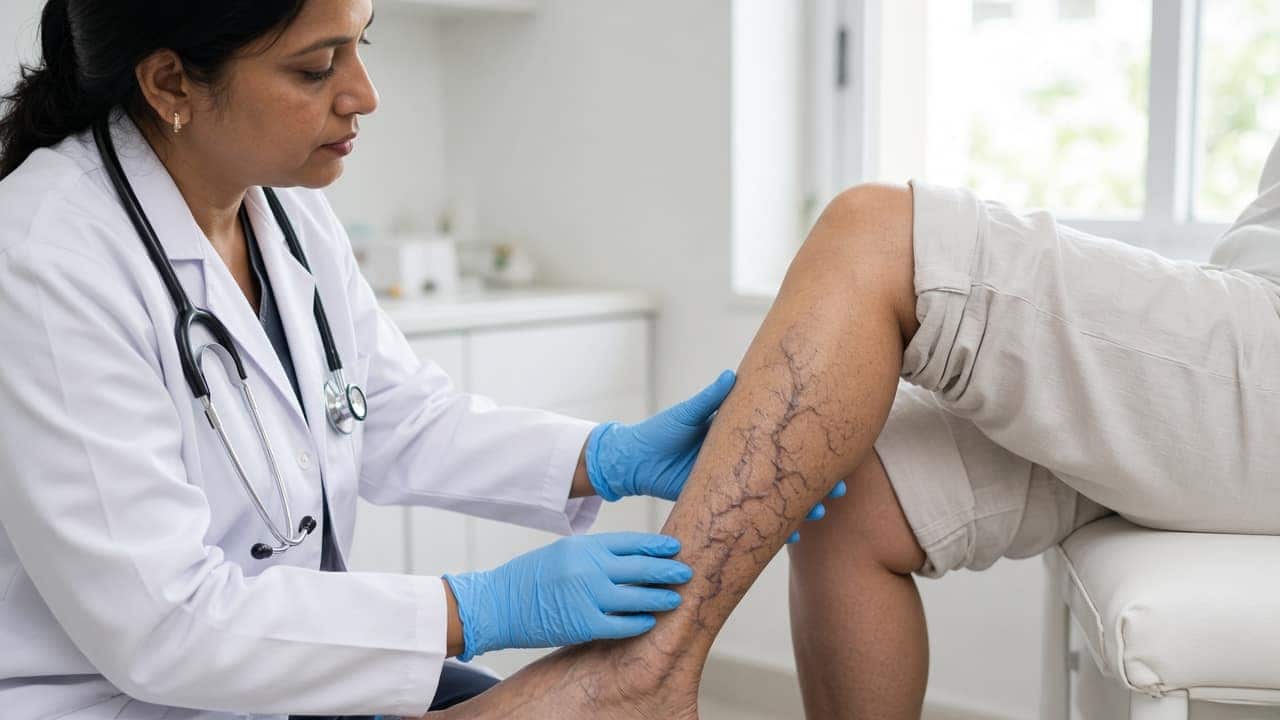
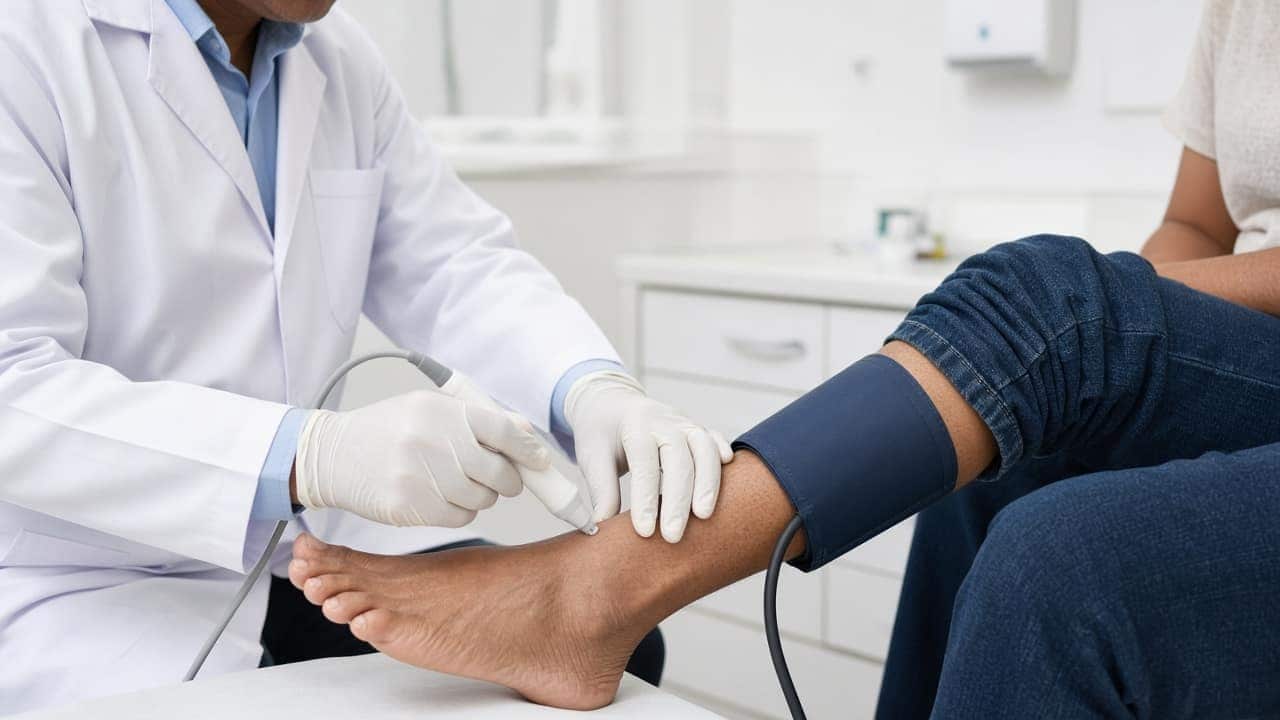
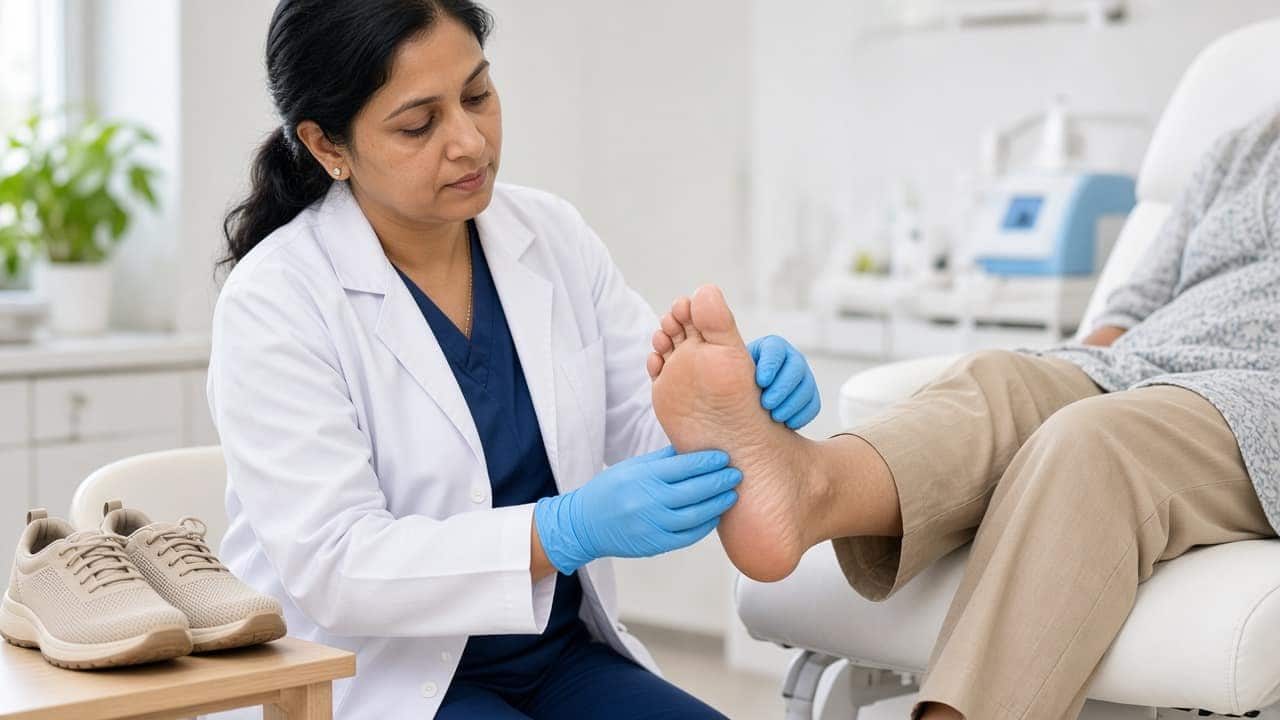
The clinician looks at depth, infection, sensation, footwear, and pulses. A probe-to-bone test, blood tests, and an X-ray are used when bone infection is possible. Circulation tests are added when healing is unlikely without better blood flow. Care of the ulcer itself is described on the diabetic foot pages.
Questions patients ask
If the ulcer does not hurt, can it wait?
No. Lack of pain often means the nerves are damaged. Painless ulcers can still be deep or infected.
Should I soak the foot?
Soaking can macerate skin and is not a treatment for an ulcer. Follow the dressing plan given after the foot has been examined.
This page is general education about vascular conditions and the way they are usually assessed. It does not diagnose a person or replace a consultation. Decisions about tests and treatment depend on an individual clinical assessment. Nothing on this website promises a particular result, a cure, or freedom from pain.